 English
 French
 German
 Spanish
 Hindi
 Italian
 Japanese
 Korean
 Norwegian
 Chinese
Giving birth in France: when more medicine is no longer enough
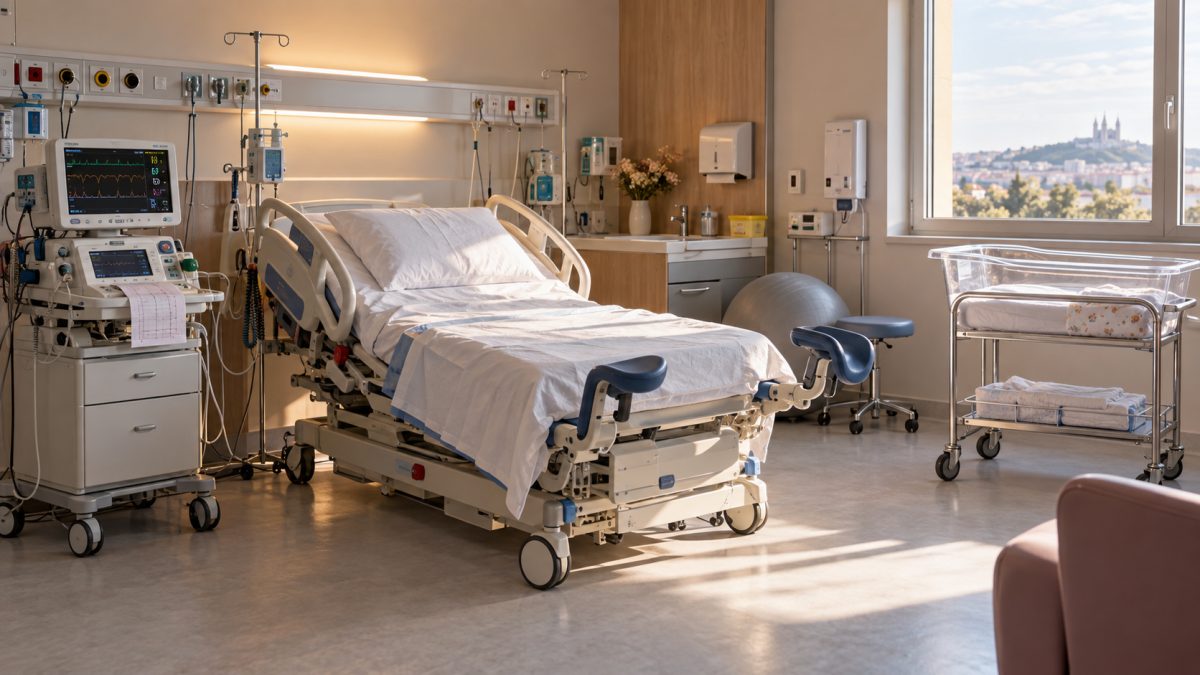
There is a paradox that is difficult to face: France has highly medicalized obstetric care, yet its perinatal indicators are not following the reassuring trajectory that such sophistication might lead us to expect. Perinatal mortality, which remained around 10.5 per 1,000 between 2014 and 2021, rose to 10.6 in 2021, 10.8 in 2023 and then 11.2 per 1,000 births in 2024. In that final year, 7,398 children were stillborn or died during their first week, out of 661,822 births.
These figures do not prove that medicine is causing more babies to die. That shortcut would be as dramatic as it is false. They do, however, force us to ask a more uncomfortable question: at what point does the accumulation of precautions, protocols and interventions stop being synonymous with additional safety?
The problem is not “medicine,” but the automatic equation of intervention with safety
The first difficulty is understanding what perinatal mortality measures. In 2024, stillbirths accounted for 82% of it, and 39% of those cases followed a medical termination of pregnancy. Prematurity also weighs heavily: 84% of perinatal deaths involve premature births. The rate reaches 125.7 per 1,000 among premature babies, compared with 2.0 per 1,000 among full-term babies.
The mother's age, the number of fetuses, gestational age, place of residence and socioeconomic conditions also matter. But Drees points out that several known factors — particularly gestational age, type of pregnancy and maternal age — explain only part of the trend observed since 2014. In other words, a grey area remains.
It is within this grey area that the question of overmedicalization deserves to be raised, cautiously. The CNRS reports that medicalization can reassure both patients and doctors without, by itself, guaranteeing the safety of childbirth and postnatal follow-up. It also highlights productivity pressures within the healthcare system and the limits of an organization built around managing maximum risk.
Two propositions must be clearly distinguished. Saying that “more interventions do not automatically guarantee better outcomes” is compatible with the available evidence. Saying that “overmedicalization is causing the current rise in mortality” is not: the causal link has not been established. That distinction changes everything.
Comparing European countries: useful, but not for telling an overly simple story
International comparison might seem to provide the ideal test. If less interventionist countries systematically achieved better outcomes, the debate would be settled quickly. Yet the available data do not support such a clear-cut conclusion.
The Euro-Peristat report, which compares 28 countries using data from 2015 to 2019, paints a mixed picture for France. The country has a controlled caesarean section rate while showing a less favorable situation for stillbirths. France also ranks 21st and 22nd in Europe for spontaneous stillbirth and infant mortality, respectively.
But one essential piece is precisely missing if this comparison is to become a demonstration: under its protocol, Euro-Peristat was unable to compare mortality after birth in France with that of other countries. France is one of eight countries out of 28 that did not provide the necessary neonatal mortality data.
It would therefore be tempting, but misleading, to pick a European country, describe it as “less medicalized,” and attribute its better outcomes to that difference alone. International comparisons show that practices vary and outcomes differ; in this case, they do not prove that intervening less causes better outcomes. Their value lies elsewhere: they prevent us from treating the French system as the only rational way to make childbirth safe.
The real bias: confusing what is visible with what is effective
An intervention is visible. An extra piece of equipment is visible. A reinforced protocol is visible. A decision not to intervene because the situation does not justify it is far less dramatic. Perhaps part of our collective difficulty in thinking about risk lies there.
This intellectual mechanism extends beyond obstetrics, without any need to claim statistical proof here in other sectors. It can be recognized as a general temptation: in justice, to imagine that adding controls necessarily makes the system safer; in education, that multiplying assessments mechanically improves learning; in finance, that every new procedure automatically reduces risk. These are analogies in reasoning, not comparisons of outcomes.
The bias consists in counting the resources deployed as though they were already results. A policy can become denser, more controlled, more documented and more technical without its ultimate objective improving at the same pace. In obstetrics, the indicator that matters is not the number of procedures available or performed: it is the health of the mother and child.
Safety may also depend on what surrounds the medical act
This perspective helps explain why the productivity pressures mentioned by the CNRS matter. A maternity unit is not merely a collection of machines and protocols. It is also an organization, available time, and a capacity for observation, follow-up and adaptation. Technically well-equipped medicine can therefore remain vulnerable to weaknesses that cannot be solved by adding another intervention.
The public response also shows that the problem is now being treated as structural as well as medical. The government has launched a mission on perinatal care. A registry of births and deaths was announced in March 2025. Parliament also adopted at first reading a three-year moratorium on maternity-unit closures.
These decisions do not point to a single cause. Rather, they reveal the extent of what we still do not fully understand.
Moving beyond the false choice between “natural” and “medical”
The debate would benefit greatly from not turning into a battle between camps. Pitting “natural” childbirth against modern medicine would miss the essential point. A caesarean section, monitoring or an intervention can obviously be indispensable. The serious question is whether each is appropriately indicated and, more broadly, whether the organization can detect genuine risk without treating every birth as though the worst-case scenario were already unfolding.
The French increase therefore does not prove that overmedicalization kills. It provides something more useful: a reason to stop taking for granted the idea that more technology necessarily means more safety.
When an indicator worsens despite an accumulation of control measures, the right response is neither to reject medicine nor to demand more of it automatically. It is to measure what actually works, compare organizational models, improve missing data and accept that an intervention can be lifesaving in one case without thereby becoming a model to be generalized.
In childbirth as elsewhere, safety is not the volume of precautions we pile up. It is the outcome those precautions produce.





